Educational illustration · Read the evidence and limitations below.
What is Icotrokinra?
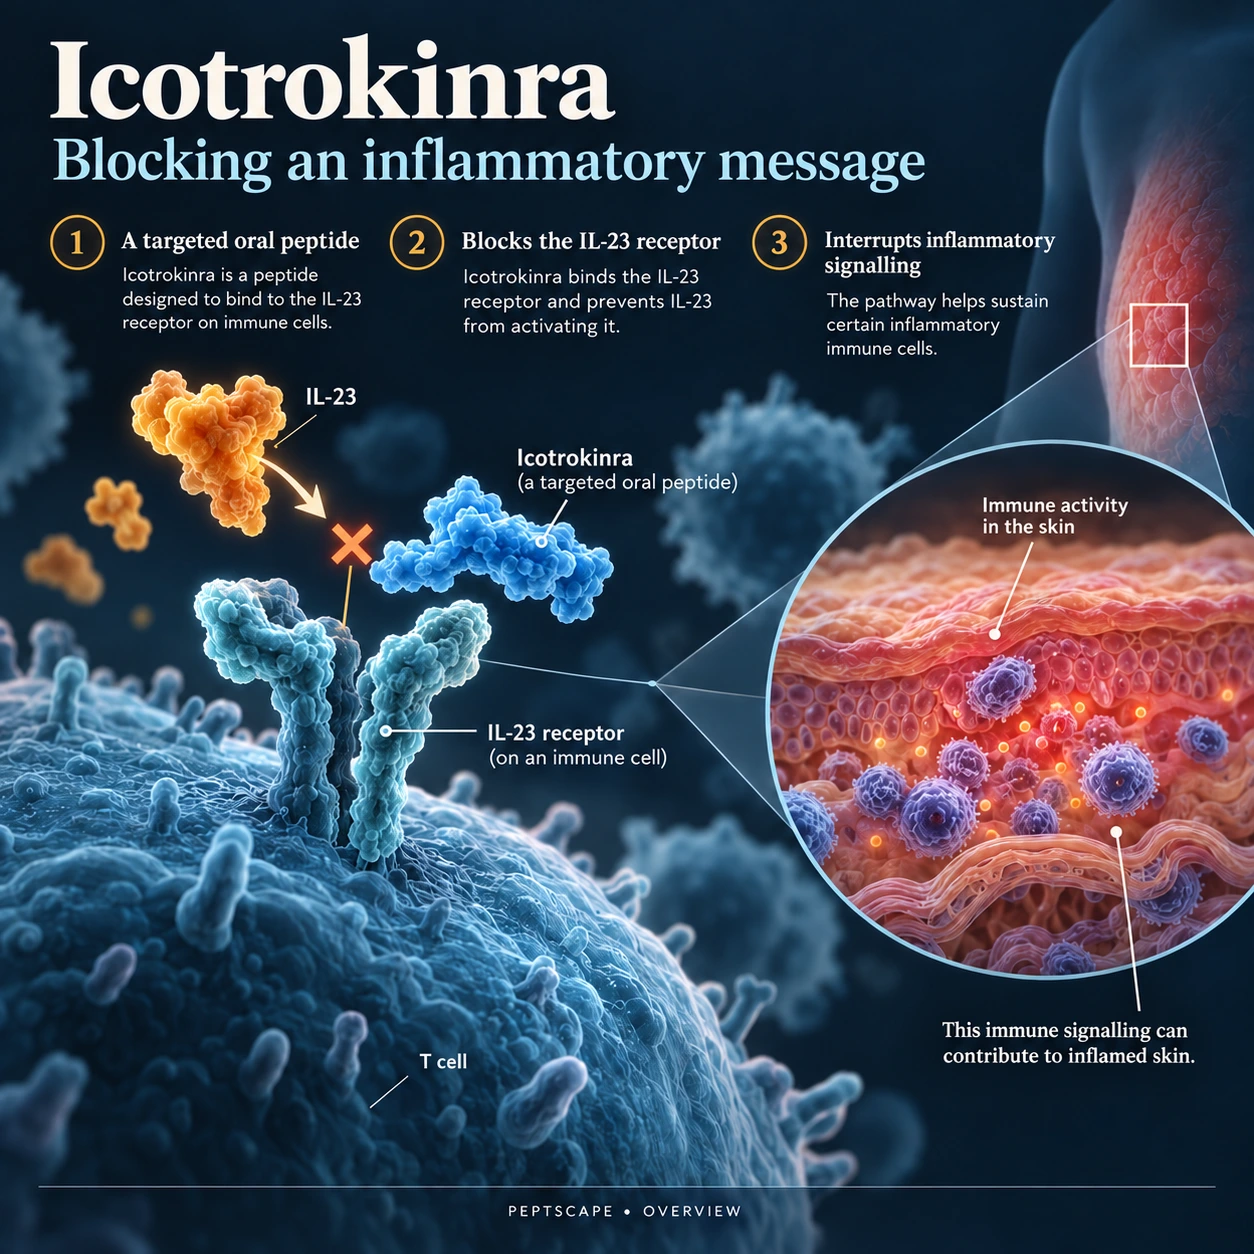
Icotrokinra is an oral peptide that blocks the interleukin-23 receptor. Interleukin-23, often written IL-23, participates in inflammatory signalling relevant to plaque psoriasis. This peptide is designed for targeted immune treatment rather than general immune stimulation or cosmetic collagen support.
The wider picture
The immune system is a coordinated network rather than a single dial that should always be turned up. It recognises threats, communicates between cells, clears damaged material and helps resolve inflammation. Excessive or misdirected activity can also damage healthy tissue. An immune-related peptide needs to be understood by the particular response it influences, rather than described simply as an immune booster.
Inflammation is a response to injury or threat. It helps recruit resources, but it also needs to settle once the problem is controlled. Reducing redness or an inflammatory marker is not always equivalent to eliminating an infection. The cause of the response matters as much as its intensity.
What it is used for
Its use concerns inflammatory skin disease, particularly plaque psoriasis in eligible patients. Psoriasis is more than dry or irritated skin: immune activity drives characteristic plaques and can occur alongside other health problems. An oral targeted peptide does not replace the need to identify the condition or review infection risks and other treatments.
Understanding the intended benefit
Infection, autoimmune disease, allergy and wound healing involve different problems. A molecule relevant to one of these does not necessarily help the others. Useful outcomes are also condition-specific: a wound closing, fewer disease flares or a particular symptom improving are not interchangeable with a change in an immune blood marker. Persistent fever, an expanding red wound or worsening breathlessness calls for an assessment of the underlying problem.
An antimicrobial effect and an immune-modulating effect describe different actions. The first concerns an organism directly; the second concerns how the body responds. A peptide may have aspects of both, but that does not make it a replacement for identifying the organism, treating the source of infection or managing an autoimmune disease appropriately.
How it works
The molecule has a ring-like structure that contributes to its suitability for oral development. It interrupts reception of an IL-23-related message rather than acting as a steroid or a general nutrient. This is an example of why some peptides can work orally, but its formulation cannot be used as evidence that unrelated peptides will survive digestion or reach their targets in the same way.
The biology in plain language
Immune cells exchange messages through receptors and signalling pathways. Some signals recruit cells, some activate them and others help quiet the response. Dose, timing, route and the condition of the tissue can influence which effects dominate. This is why activity against a microbe in a laboratory does not automatically describe an effective treatment for an infection, and why suppressing an inflammatory signal does not establish that every other immune function is preserved.
Nutritional adequacy supports normal immune function, but megadoses do not reliably turn the system into a stronger defence. Protein, energy and correction of genuine deficiencies serve different purposes from a targeted immune medicine. Existing immunosuppressive treatment, autoimmune disease and a history of serious infection can change the context, so an immune peptide should not be added as a routine wellness extra.