Educational illustration · Read the evidence and limitations below.
What is GHRP-6?
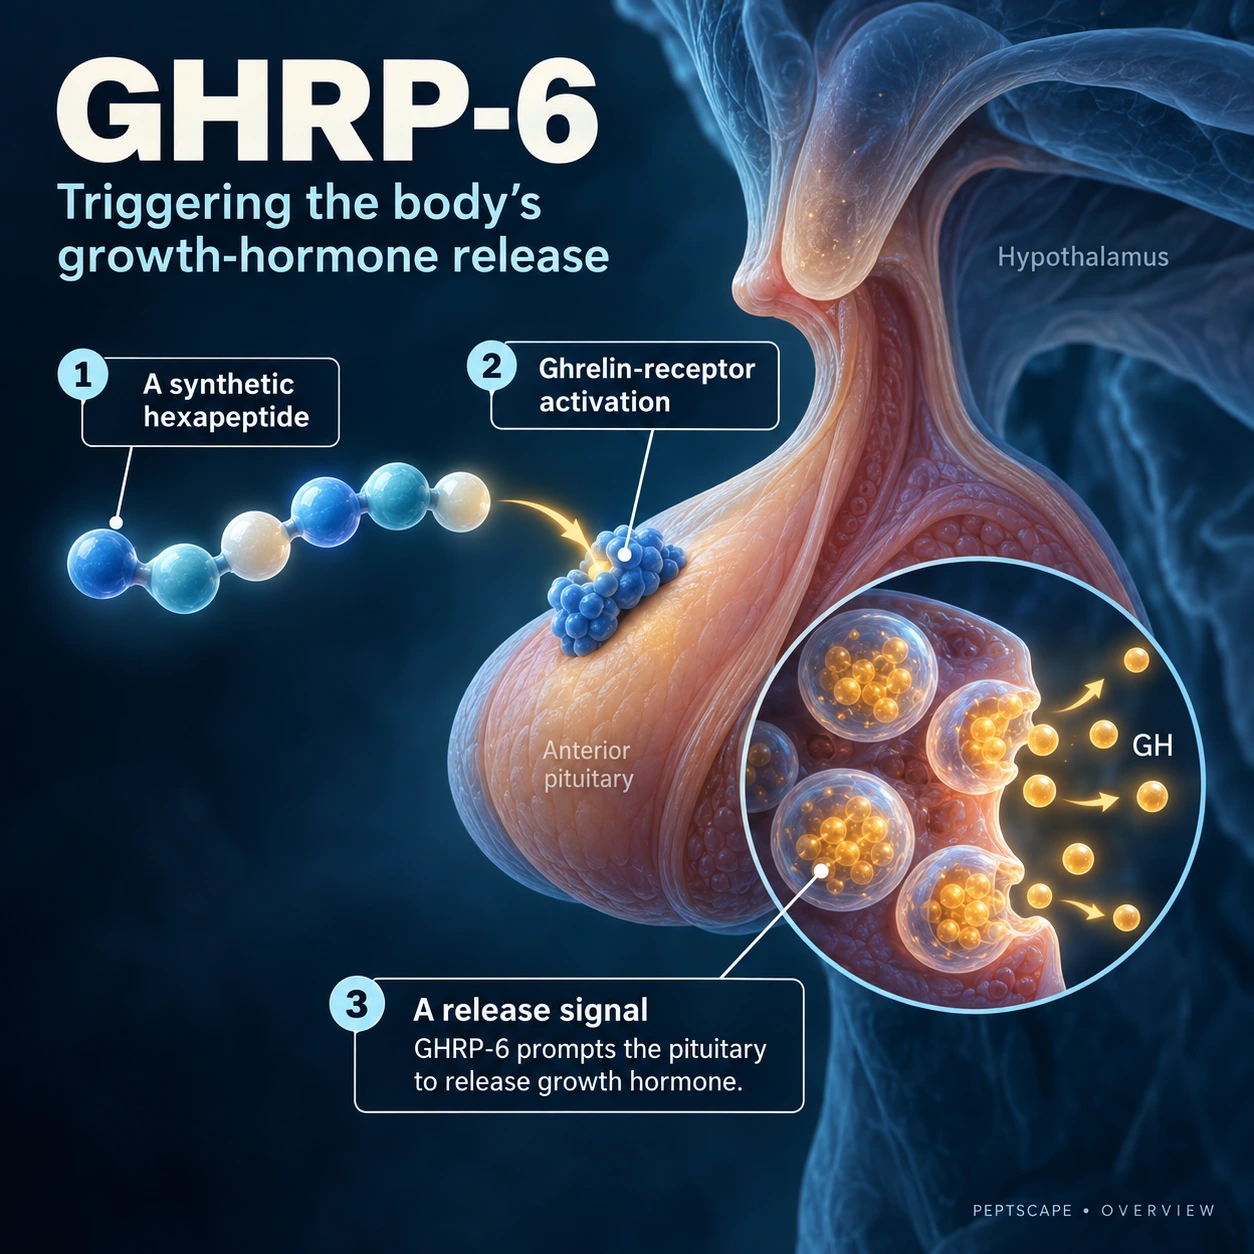
GHRP-6 is a synthetic six-amino-acid peptide that stimulates growth hormone release through the ghrelin receptor. Its especially recognisable feature is appetite stimulation. It belongs to the same broad receptor family as GHRP-2 and hexarelin, but it is not interchangeable with either and is not a form of injected growth hormone.
The wider picture
Growth hormone is released by the pituitary, a small gland beneath the brain. Release normally comes in pulses rather than as a constant stream. Growth hormone then influences several tissues and stimulates production of IGF-1, another growth-related signal. Asking the pituitary to release growth hormone is different from injecting growth hormone itself. It also requires a pituitary capable of responding.
Growth hormone and testosterone are different hormones. Both can influence body composition, but they act through different receptors and are assessed differently. A growth hormone-related peptide does not automatically correct low testosterone, and a body-composition complaint does not identify which hormonal system, if any, needs treatment.
What it is used for
Its experimental applications include appetite, body composition and recovery-related goals. The appetite effect deserves a prominent place in the explanation: increased hunger may be unwelcome when the goal is fat loss, and overeating can outweigh any hoped-for change in metabolism. The feeling of hunger is a receptor effect, not a measurement of the amount of muscle being built. A response in growth hormone also does not establish improved injury healing or sleep quality.
Understanding the intended benefit
Interest in this pathway includes body composition, recovery and the effects of ageing. Those goals need to be separated from treatment of a diagnosed hormone deficiency. More circulating growth hormone does not automatically mean more strength, better sleep or faster healing. Changes in body weight may include fluid retention. Swelling, hand tingling, joint discomfort and changes in glucose control should not be mistaken for useful muscle growth.
IGF-1 is often discussed alongside growth hormone because it reflects part of the downstream response. It is not a direct measurement of the strength of every growth hormone pulse. Age, nutritional status, liver function and other conditions can influence interpretation. Chasing the highest possible number is not the same as finding a useful and appropriate physiological response.
How it works
GHRP-6 influences a signalling system normally used by ghrelin, a hormone associated with hunger and meal-related physiology. The receptor is involved in several processes, so the compound should not be understood as a single-purpose muscle signal. GHRH-type peptides such as sermorelin act at another receiving point; combining the two approaches is a separate treatment question, not an automatic improvement. IGF-1 and glucose measurements can describe downstream effects but must be interpreted with the person's clinical context. Hormone stimulation is a biological action; a useful treatment result still has to concern how the person feels or functions.
The biology in plain language
The pathway has feedback controls. The brain helps regulate pituitary release, and signals from downstream tissues influence the next response. Sleep, meals, age, illness and other hormones all affect this system. A single laboratory value therefore needs context. The timing of a blood sample and whether the test measures growth hormone or IGF-1 matter. The two measurements describe different parts of the same network and cannot be substituted for one another.
Recovery includes repair of tissue, replenishment of fuel and recovery from fatigue. Sleep and sufficient nutrition support these processes, while progressive rehabilitation supplies the loading needed for injured tissue to regain function. A hormone-related intervention does not replace those distinct inputs. A peptide stack with several agents acting on the same release pathway may also duplicate effects rather than provide separate benefits.