Educational illustration · Read the evidence and limitations below.
What is Adipotide (FTPP)?
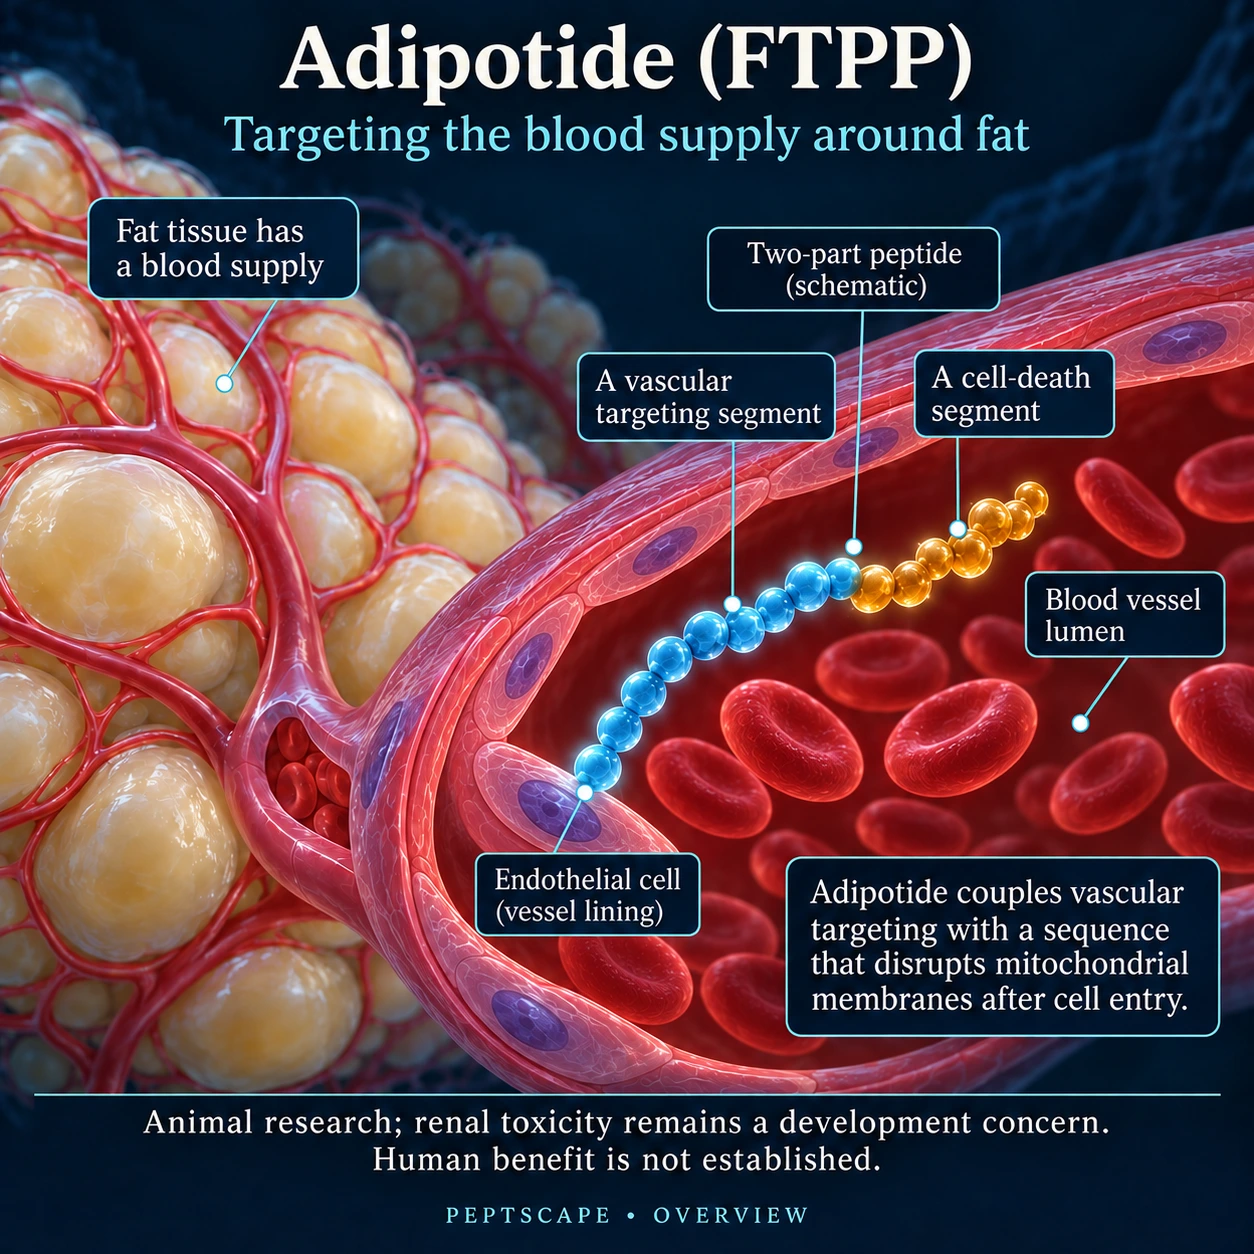
Adipotide, also called FTPP, is an experimental compound designed to target blood vessels supplying white fat. Its approach differs sharply from reducing appetite or changing the release of growth hormone. It combines a targeting component with a component intended to damage the selected cells.
The wider picture
Fat metabolism is the way the body stores, releases and uses fat. It is different from appetite: a compound can act on a metabolic pathway without making a person feel less hungry. It is also different from losing water, which can move the scale quickly without removing much stored fat. Understanding the target helps explain why metabolic compounds cannot be compared simply by how many kilograms are lost in the first week.
There are several fat stores in the body. Subcutaneous fat sits beneath the skin; visceral fat surrounds internal organs; liver fat is stored within the liver. They can respond differently during weight change. A smaller abdomen is encouraging information, but it is not an exact measurement of any one compartment. A body-composition claim should say which outcome it actually concerns.
What it is used for
The goal is reduction of fat tissue, but targeting its blood supply introduces risks that are different from ordinary weight-management treatment. Kidney injury is a significant concern in the development record. Adipotide should not be described as a precision fat-removal tool that leaves the rest of the body unaffected, or as a proven method of removing fat from a chosen body area.
Understanding the intended benefit
For body composition, separate total weight, waist size and physical function. A smaller waist can be useful, but a tape measure cannot tell precisely how much fat came from around the organs rather than beneath the skin. Strength and everyday activity help reveal whether a weight change is accompanied by loss of useful muscle. Fatigue, persistent weakness and difficulty eating are problems to investigate, not signs that a metabolic intervention is working especially well.
Insulin resistance means that tissues respond less effectively to insulin, so the body may need more insulin to handle the same glucose load. This can coexist with normal glucose results for a time. It is different from simply eating too much sugar on one occasion. A metabolic compound's effect on insulin-related markers and its effect on body weight therefore answer different questions.
How it works
The targeting component recognises a structure associated with blood vessels in fat tissue. The linked cell-disrupting component is intended to act after delivery. Selectivity is the central challenge: biological targets are not necessarily unique to one desirable location. This is why a substantial weight change alone cannot establish a favourable balance of benefit and harm.
The biology in plain language
Cells respond to several overlapping messages about food availability and energy demand. An enzyme is a protein that helps a chemical reaction happen; a receptor receives a signal; a hormone carries a message between tissues. Changing one of these steps can affect more than one organ. This is why a plausible fat-metabolism mechanism is a starting point for understanding a compound, rather than a guarantee of a particular weight-loss result.
Sustainable fat loss also depends on the balance between energy intake and expenditure over time. A pathway affecting fat cells does not make meals, activity or muscle maintenance irrelevant. Protein supports tissue maintenance, and resistance exercise supplies a different signal from a metabolic compound. These are complementary physiological needs, not a claim of a proven supplement-and-peptide synergy.