Educational illustration · Read the evidence and limitations below.
What is Teduglutide?
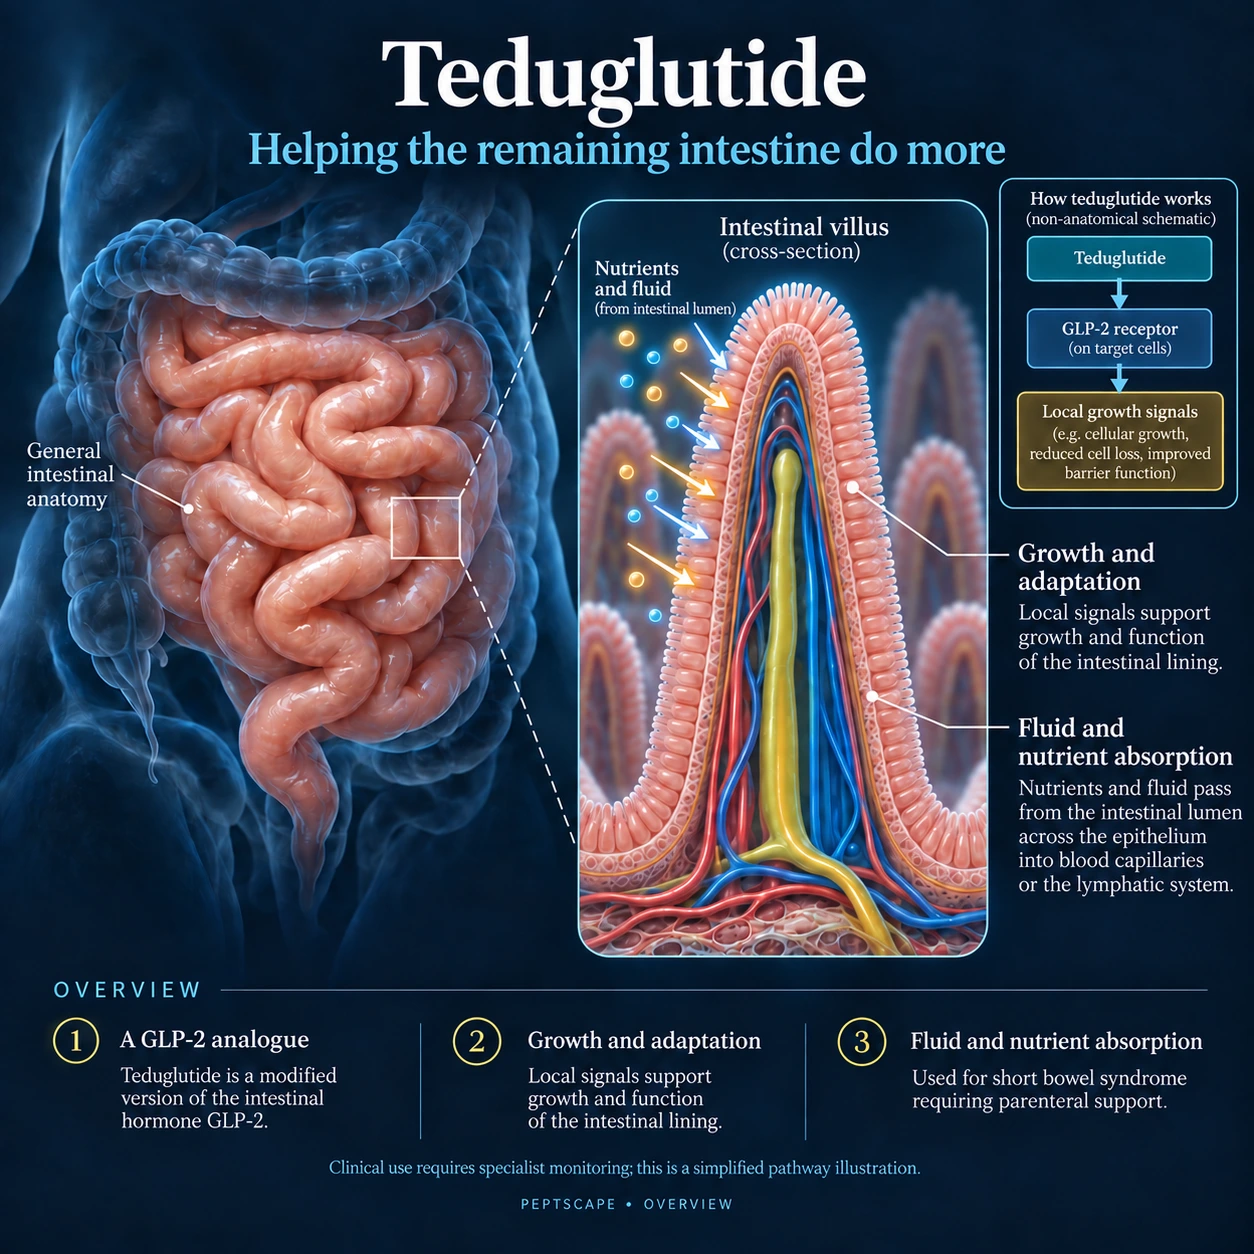
Teduglutide is a modified GLP-2 peptide used in selected patients with short bowel syndrome who depend on parenteral support. It acts on intestinal adaptation and absorption. It is not a GLP-1 weight-loss drug and is not intended simply to make a healthy digestive tract absorb more nutrients.
The wider picture
GLP-2 is a gut hormone involved in maintaining the intestinal lining and supporting absorption. It has a different main role from GLP-1, the hormone better known for appetite and glucose control. Similar names do not mean similar uses. Increasing the intestine's ability to absorb fluid and nutrients is a different objective from reducing appetite to support weight loss.
The remaining bowel adapts after resection, but its ability to do so depends on which sections remain and whether the colon is in continuity. The same bowel length can therefore have different practical consequences in different people. Absorption is a function of anatomy and tissue health, not just a peptide receptor response.
What it is used for
The practical goal is to maintain hydration and nutrition while reducing the amount of outside support needed where possible. This requires monitoring of fluid balance and intestinal complications. A change in absorption can also affect the handling of other medicines, and support should not be withdrawn simply because appetite or stool pattern changes.
Understanding the intended benefit
Short bowel syndrome occurs when the remaining intestine cannot absorb enough after major loss of bowel. Some people need fluids or nutrition delivered into the bloodstream. In that setting, reducing the amount of outside support can be a meaningful benefit even if the person still needs treatment. This is not equivalent to treating ordinary bloating or improving a healthy person's digestion.
A person can lose fluid through the bowel while also developing swelling from another problem. Body weight alone is therefore not a sufficient guide to fluid needs. Teams managing intestinal failure use symptoms, intake and output, weight and laboratory results together. The aim is reliable hydration and nutrition rather than the fastest possible withdrawal of support.
How it works
The modification helps the peptide resist rapid breakdown compared with natural GLP-2. Its receptor activity supports the intestinal lining's adaptive response. The anatomy of the remaining bowel and the person's disease history matter directly to that response. Teduglutide, apraglutide and glepaglutide share a target family but have different molecular and exposure properties.
The biology in plain language
The intestinal lining adapts over time. Its surface area, blood flow and movement all influence how much is absorbed. GLP-2-based treatment is intended to support parts of that adaptation. As absorption changes, fluid balance and other medicines can change too. Adjustments to intravenous support require the treating team: maintaining hydration, kidney function and nutritional status is more important than pursuing a particular reduction in litres on its own.
As the intestine absorbs more, previously appropriate amounts of fluids, nutrients or other medicines may need review. That is a consequence of the intended biological change, not necessarily treatment failure. The preparation-specific monitoring plan matters because GLP-2-based treatment affects a working organ system over time, rather than providing a brief correction of one symptom.