Educational illustration · Read the evidence and limitations below.
What is Liraglutide?
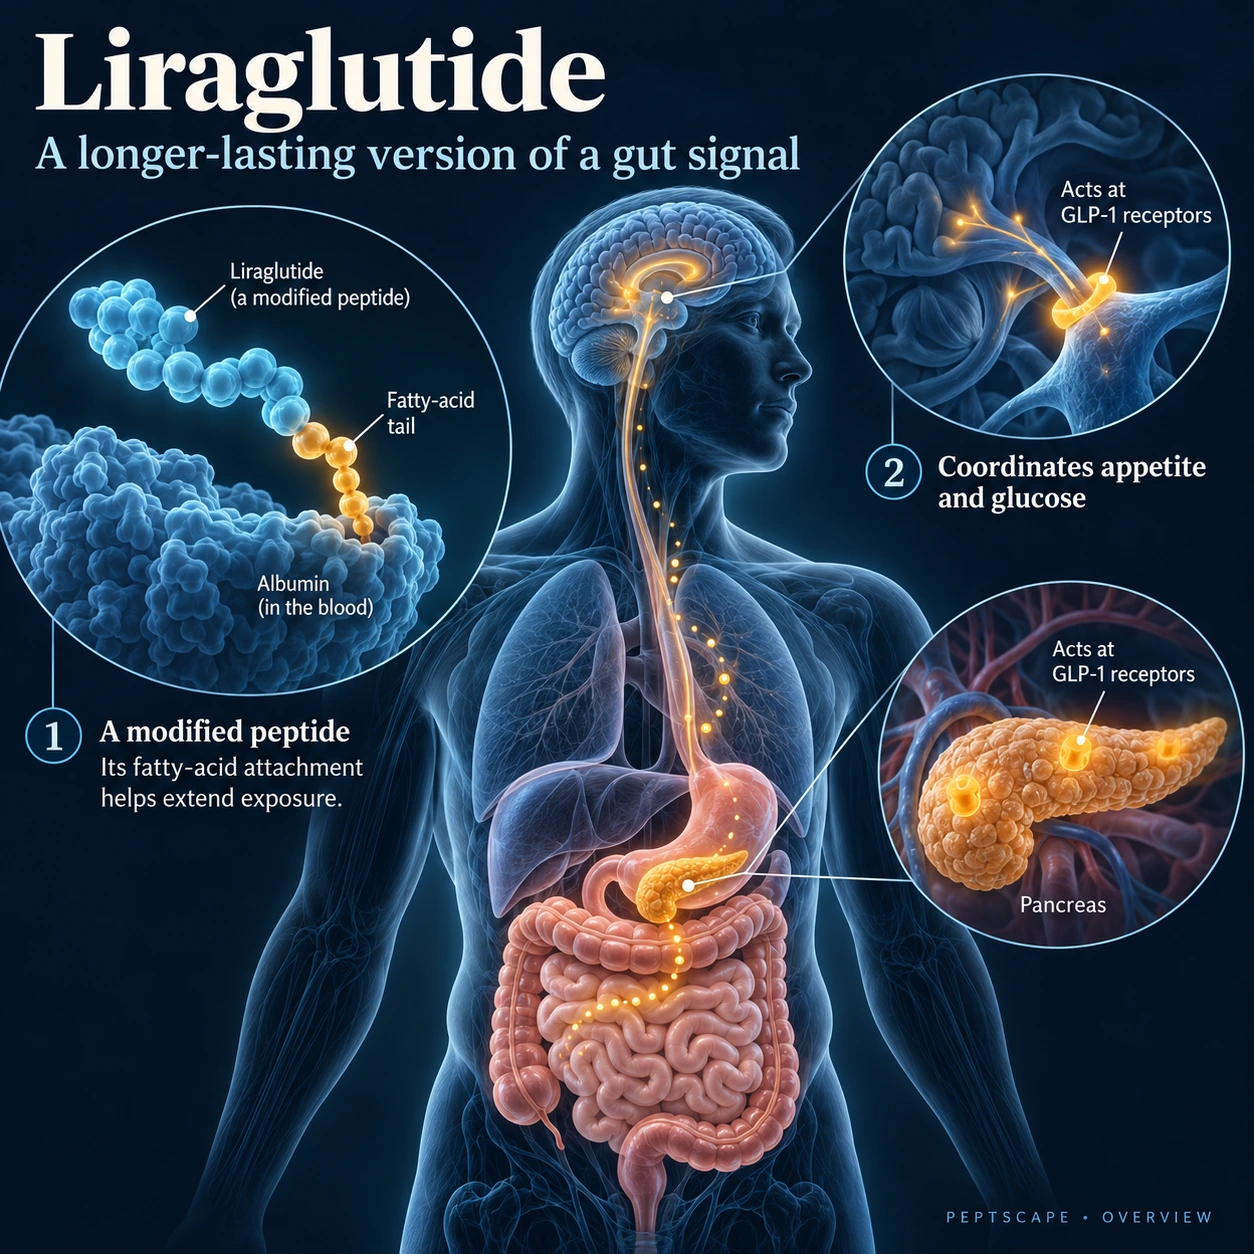
Liraglutide is a GLP-1 receptor agonist used in glucose management and weight-management treatment. It is the active peptide, independent of the brand name of a particular finished product. Its molecular design extends activity beyond that of native GLP-1, but it has a different exposure pattern from weekly analogues.
The wider picture
Appetite is controlled by communication between the digestive tract, pancreas and brain. Gut hormones help tell the body that food has arrived and help coordinate the handling of that meal. Peptides acting on these signals can influence hunger, fullness and blood glucose. They do not physically dissolve fat, and the amount of a peptide in milligrams does not measure its strength relative to a different molecule.
Hunger, fullness and cravings are not identical. Hunger is the drive to eat; fullness is the response during and after a meal; cravings can be tied to reward, habit or circumstances. A treatment can change one more than another. Being able to identify the change makes the experience easier to describe and helps avoid interpreting every digestive sensation as appetite benefit.
What it is used for
Its uses include helping reduce appetite and improving glucose-related outcomes in appropriately selected patients. Diabetes and weight-management presentations can have different instructions. The existence of both applications does not mean that any research-labelled vial has the same concentration, quality or dosing instructions as either presentation.
Understanding the intended benefit
Weight management involves more than the number on a scale. Fullness may make smaller meals easier, but those meals still need enough protein, fluid and other nutrients. Waist measurements, strength, bowel comfort and the ability to carry out normal activities provide useful context. Ongoing vomiting or an inability to drink is not a stronger version of appetite control. Those symptoms need prompt attention rather than being accepted as the price of losing weight.
The first changes on the scale can include water and stored carbohydrate as well as fat. Over longer periods, loss of lean tissue also matters. Adequate protein and resistance activity help support muscle maintenance, but they do not guarantee that every kilogram lost is fat. Gradual changes in waist, strength and function give a more useful picture than comparing isolated daily weights.
How it works
Liraglutide activates the GLP-1 receptor and has a fatty-acid modification that contributes to binding and prolonged exposure. It is not a dual GIP or glucagon agonist. Its daily treatment pattern reflects properties of the peptide and its formulation; a schedule should not be changed to weekly simply because another GLP-1 peptide is used that way.
The biology in plain language
A receptor is a receiving point on a cell. GLP-1, GIP, glucagon and amylin receptors participate in different parts of appetite and metabolic control. Combining receptor actions is intended to change the overall response; it does not mean that the strongest possible stimulation of every pathway is desirable. Duration also depends on the molecule's design and preparation. An oral tablet, a research vial and a long-acting injection cannot be compared by assuming that equal milligrams deliver equal exposure.
A longer-acting peptide can continue to have effects after an administration is missed or treatment is stopped. Absorption and breakdown determine blood exposure, while eating patterns and downstream responses may change on another timeline. This is why an extra dose should not be improvised to compensate for an uncertain response. The specific preparation's instructions govern missed-dose and restart decisions.