Educational illustration · Read the evidence and limitations below.
What is HMG?
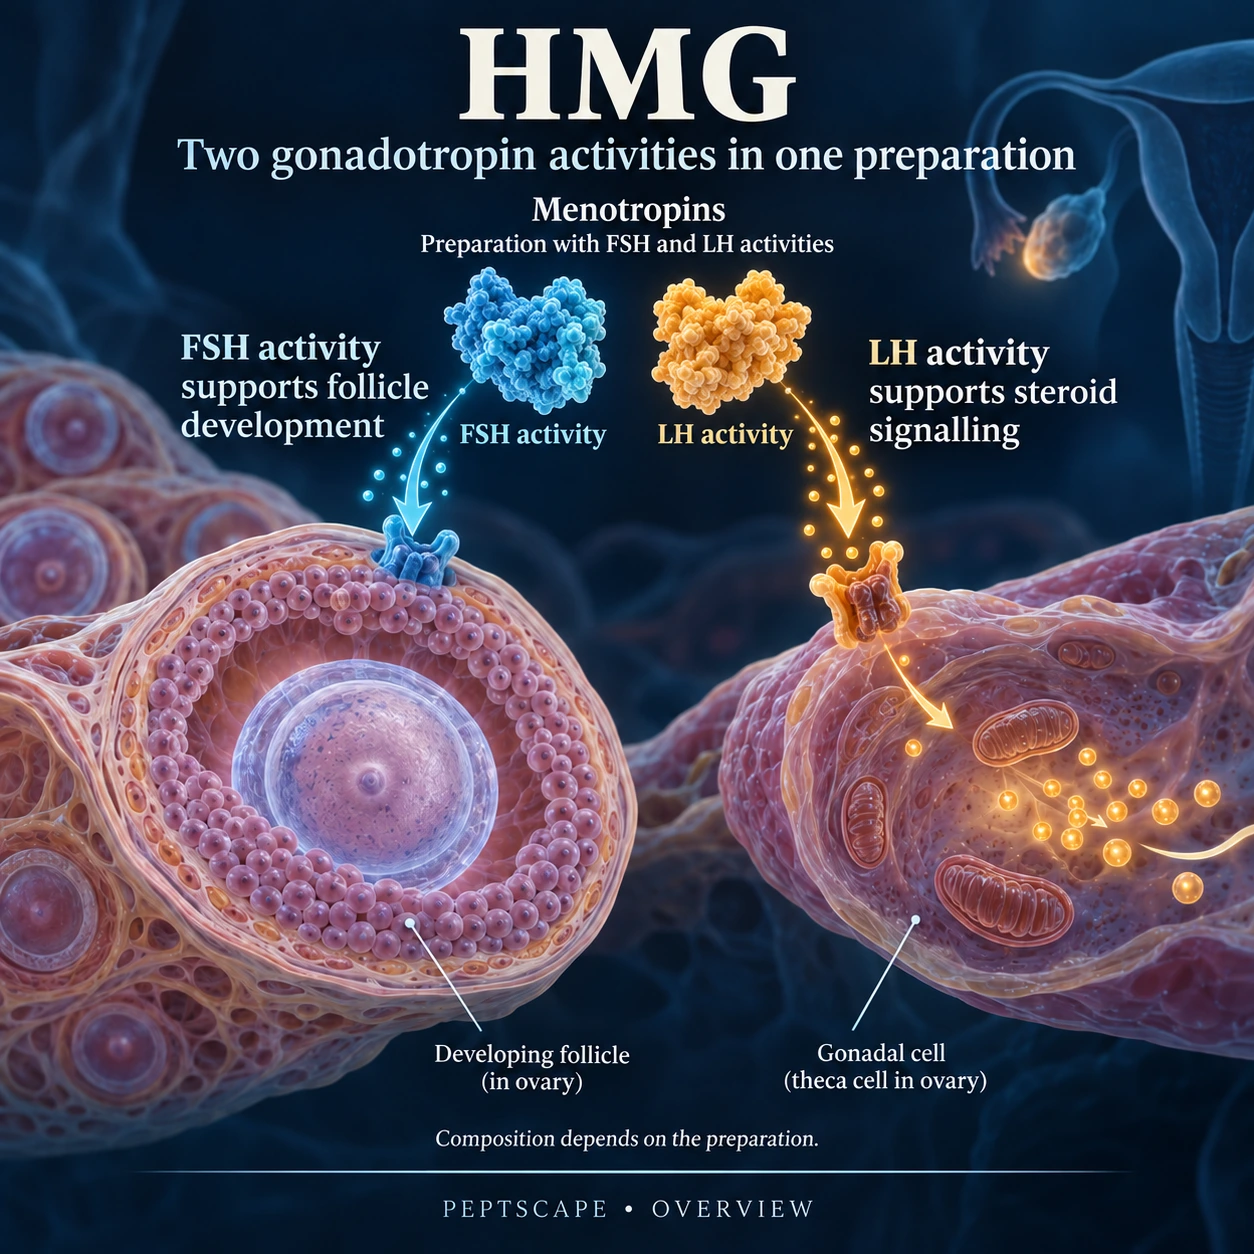
HMG, or human menopausal gonadotropin, refers to menotropin preparations providing FSH activity together with LH-related activity. It is a reproductive hormone preparation, not a single small peptide for general wellness. The balance of activity and the finished formulation matter.
The wider picture
Reproductive hormones form a communication chain. The brain signals the pituitary; the pituitary releases LH and FSH; the ovaries or testes respond. Feedback then travels back through the system. LH and FSH have different roles, and replacing or stimulating one signal is not the same as correcting every possible cause of infertility or low sex-hormone levels.
The reproductive hormone chain contains several checkpoints. An upstream signal may be present while the pituitary or gonads cannot respond adequately. Conversely, those organs may function but receive insufficient stimulation. Knowing where the problem lies explains why two people with a similar hormone result may need different care.
What it is used for
Its uses include controlled ovarian stimulation and selected infertility treatment. Follicle development needs monitoring because too strong a response can cause ovarian hyperstimulation and increase the chance of multiple pregnancy. This is different from trying to raise a laboratory hormone value in isolation. Severe abdominal swelling, pain or breathlessness during fertility treatment needs prompt review.
Understanding the intended benefit
Fertility, sexual desire and hormone deficiency are separate questions. A change in a hormone measurement does not automatically improve sperm production, ovulation or sexual wellbeing. The timing of testing matters, and fertility assessment may involve both partners. Treatment aimed at inducing follicle growth or ovulation needs monitoring because the number and size of developing follicles affect both benefit and risk.
Fertility outcomes take time. Sperm production develops over a much longer interval than a short-lived hormone spike, while follicle monitoring follows the stages of an individual treatment cycle. Daily impressions of energy or libido cannot replace those assessments. A treatment record should distinguish the purpose of each hormone and the planned monitoring point.
How it works
FSH supports follicle development, while LH-related activity participates in hormone production and reproductive function. Supplying these signals acts further down the chain than gonadorelin. HMG, recombinant FSH and HCG therefore have different roles even when they appear in the same fertility plan. Their units and timing are not interchangeable.
The biology in plain language
The pattern of stimulation can be as important as the amount. Pulses, a sustained infusion and occasional injections may send different messages to the same receptor system. Some treatments act upstream at the pituitary, while others act directly at the gonads. A vial labelled in international units is describing biological activity; it is not describing the unit marks on an insulin syringe. Product identity and concentration must remain separate from the intended hormonal goal.
More stimulation is not automatically a better response. Excessive ovarian stimulation can cause serious illness, and attempts to optimise one sex-hormone value can alter feedback elsewhere in the chain. Existing testosterone or other hormone treatment may also change fertility. These interactions make the full treatment history more informative than a single peptide name or a single blood result.