Educational illustration · Read the evidence and limitations below.
What is ARA-290 (Cibinetide)?
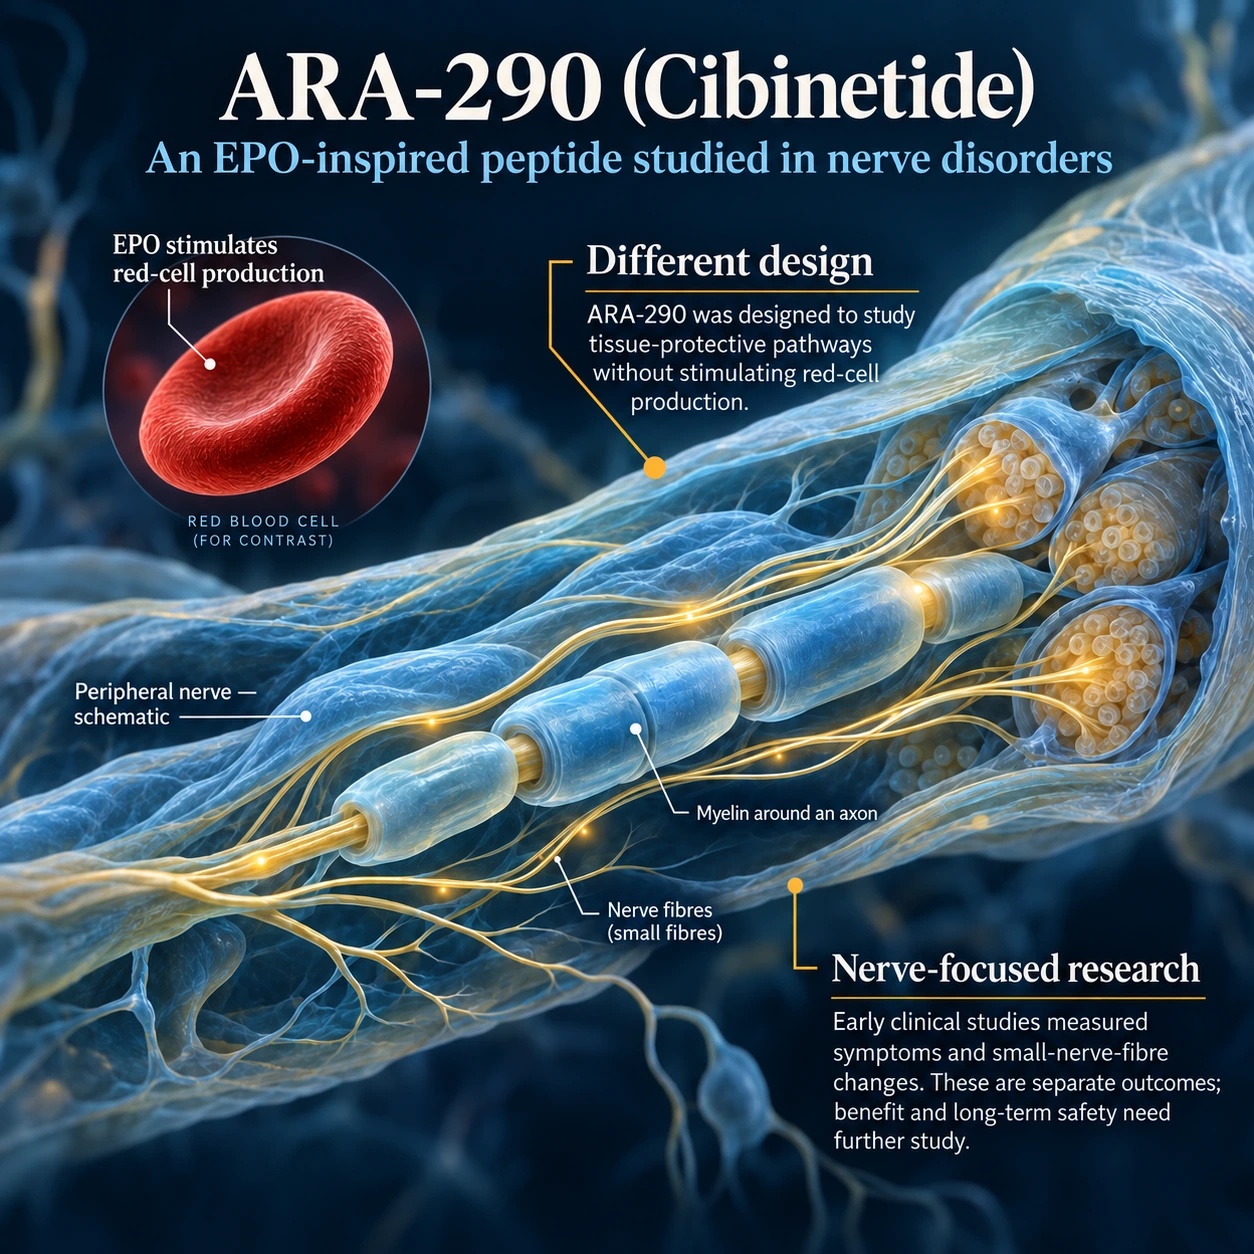
ARA-290, also called cibinetide, is a short peptide derived from part of erythropoietin's structure. It was designed to explore tissue-protective signalling without reproducing the red-blood-cell stimulation associated with EPO. It is not an anaemia treatment or a substitute for erythropoietin.
The wider picture
Peptides are short chains of amino acids, but their effects depend on the order of those amino acids and any chemical modifications. Two compounds with similar names may have different targets. An added chemical group, a reversed sequence or a different terminal form can change how a molecule interacts with cells. The name of a parent peptide does not fully describe a derivative.
A chemical identity can include more than the sequence. Some peptides have altered amino acids, capped ends, salts or attached groups. These details can affect breakdown and interactions with tissue. A complete name or analytical identity is therefore more informative than the broad category research peptide.
What it is used for
Its main area of interest is nerve injury, particularly small-fibre neuropathy. Small nerve fibres carry pain and temperature signals and contribute to automatic body functions. Burning, tingling and altered sensation can reflect damage to these fibres, but similar symptoms can have other causes. ARA-290's repair-related rationale differs from simply numbing pain.
Understanding the intended benefit
An experimental use describes the goal of development, not an assurance of a particular result. It helps to ask a concrete question: is the aim to change pain, tissue repair, metabolism or a laboratory marker? Those outcomes should not be substituted for one another. An effect on cells does not explain by itself how a person would feel or function.
A useful explanation separates the intended target from the hoped-for outcome. A target may be a receptor, an enzyme or a protein interaction. The hoped-for outcome might be less pain, improved function or a change in disease activity. Understanding the connection between the two helps avoid treating a promising mechanism as a completed treatment claim.
How it works
The design aims at a tissue-protection signalling system associated with the erythropoietin receptor family. Separating tissue signalling from red-cell production is the key idea, not increasing oxygen-carrying capacity. Pain scores, nerve structure and metabolic measurements describe different outcomes; an improvement in one should not be treated as proof that all nerve function has been restored.
The biology in plain language
The relevant mechanism begins with the exact molecule. Receptor activity, entry into tissue and the time a molecule remains intact all influence its behaviour. A research-labelled product needs a clear identity before results for another preparation can be applied to it. Practical decisions about preparation and administration require a defined formulation; they cannot be supplied by extending a mechanism diagram into a personal schedule.
The amount present in a vial, the amount delivered and the amount reaching a target are different. Absorption and distribution lie between them. Changing the route or attaching another chemical group can change those steps, but does not provide a simple conversion factor. This is why practical instructions need to match an identified preparation rather than a generic name alone.